End-to-end healthtech product development lifecycle

The end-to-end healthtech product development lifecycle runs from problem definition to post-market operations, with gated phases for clinical value proof, compliance architecture, EHR integration, trials, and scale. As of 2025, 2026, AI features, consent modeling, and integration approvals have become the critical path in many builds, so teams must sequence evidence before code.
Key takeaways
- Treat integration, consent, and compliance as design inputs at Day 1, not as a checklist at launch.
- Plan an integration-first MVP that reads safely before it writes, then add writebacks with bounded scope and auditability.
- Define clinical value and safety claims early because they decide your data model and evaluation protocol.
- Budget for approvals and site operations as a separate track from engineering to avoid idle sprints.
- For AI features, operationalize dataset provenance and model monitoring before scaling users.
What has changed in 2025, 2026 for this lifecycle?
AI features and their validation moved from optional to expected in many categories, and EHR integrations matured just enough to make read-first pilots viable at more sites. As of September 2026, the FDA had authorized over 1,600 AI-enabled medical devices, which signals more buyers asking how AI is governed post-deployment.
In practice, this changed the critical path. Two years ago, feature velocity could mask weak consent and logging. Since mid-2025, health systems have tightened data-use approvals, and vendor marketplaces scrutinize app scopes more carefully. Teams that front-load consent models, EHR data provenance, and audit trails move faster through legal and InfoSec. Those that code first often stall when the second pilot site asks for traceability, not features.
The lifecycle at a glance
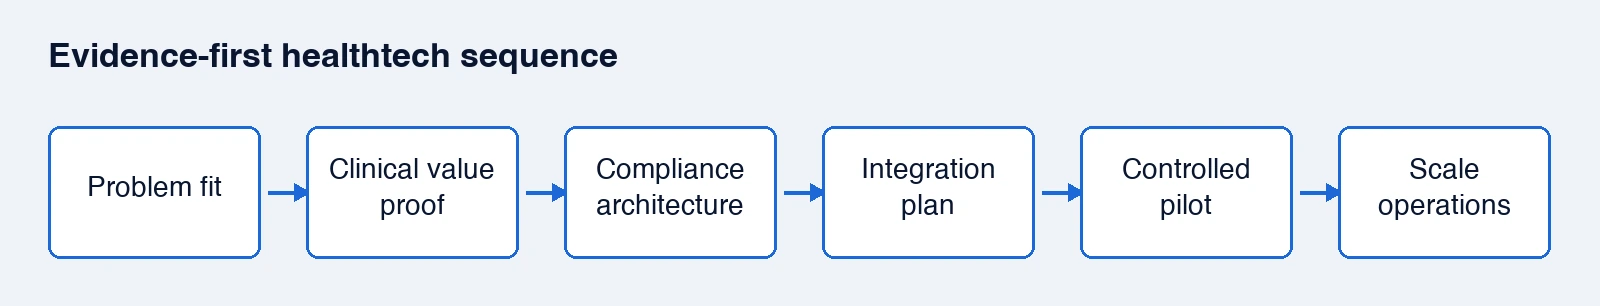
The modern lifecycle has six gates: problem fit, clinical value proof, compliance architecture, integration path, controlled pilot, and scale. Each gate asks for evidence that can be reviewed by clinicians, InfoSec, and operations, not just a demo.
A simple way to reduce rework is to define the observable unit of value early. For example, if your value is missed-appointment reduction, then your core event is a scheduled visit with a show or no-show outcome. That decides your data rights request, the EHR resources you must read, and what, if anything, you need to write back.
How do you prove clinical value before you build deeply?
You run a narrow evaluation on existing data or read-only integrations to confirm the problem and the proxy for outcomes. The goal is to lock the hypothesis and the data model before heavy implementation.
Teams often start with a read-only slice from an EHR, scheduling system, or claims feed to test feasibility. A simple example is measuring baseline throughput or care gaps in one clinic. If AI is in scope, capture ground-truthing and reviewer agreement methods early. That gives you the acceptance tests for your MVP and informs what must be audited later.
Where does compliance architecture enter the plan?
It enters before sprint 1 because it shapes data flows, logging, and who can do what. If you add it after MVP, you will rewrite core paths.
Design what data moves, who consents, where it is stored, and how you prove access was appropriate. That includes traceable identity, role-based scope, encryption in transit and at rest, and immutable audit logs. For EHR-connected apps, model writebacks as capabilities with preconditions and provenance. When the second site asks how you prevent cross-tenant access or how you revoke a stale consent, you will have an answer you can demo.
How should EHR integration sequence in the lifecycle?
Start with read-first, evented reads, then add constrained writes with explicit preconditions and site-configurable scope. This sequencing keeps InfoSec engaged and avoids site-level blockers.
Read-first reduces clinical risk and approval burden. Evented reads with signed provenance let you reconcile discrepancies and debug faster. Constrained writebacks come last with guardrails like queueing, retries, and rollbacks. This pattern also lets you swap vendors without rewriting the whole app. For a deeper dive on vendor specifics, see these EHR integration guides for Epic, athenahealth and more.
What are the real gates, evidence, and blockers?
Each gate needs a specific artifact. Teams that name these artifacts up front cut negotiation cycles with clinics and partners.
| Lifecycle gate | Evidence to collect | Typical blockers | Fast path tactic |
|---|---|---|---|
| Problem fit | Quantified pain, defined user, measurable outcome | Vague buyer, shifting scope | One-line value metric and proxy outcome |
| Clinical value proof | Retrospective cut or read-only pilot results | Data access delays, unclear ground truth | Pre-negotiate minimal read-only scope |
| Compliance architecture | Data-flow diagram, consent model, audit plan | Late security review, rework of core paths | Threat model before sprint planning |
| Integration plan | Vendor program path, endpoints, site onboarding steps | Per-tenant approvals, sandbox drift | Read-first MVP with signed provenance |
| Controlled pilot | Success criteria, rollback plan, uptime SLOs | Competing clinic priorities, change fatigue | Two-site pilot with staggered rollout |
| Scale operations | Monitoring, incident runbooks, release policy | Noisy alerts, slow hotfix path | Versioned APIs and feature flags |
How do budgets and timelines map to these gates?
You budget for two parallel tracks: engineering and site operations. The operations track covers approvals, contracting, identity provisioning, and training, which can run longer than code.
Treat advisory and architecture as early spend, not a late fix. For planning purposes, advisory from specialized fractional CTOs can start near $2,000 per month, so budget early to avoid idle teams while approvals run. Timeline risk usually comes from site onboarding calendars, identity provisioning, and the first writeback. You can shorten the path by delivering a high-signal read-only pilot while approvals for writes proceed.
MVP scope: what belongs and what waits?
Keep MVP scope to read-only or minimally invasive writes that are reversible, with value proven by a clear metric. Anything that alters clinical workflow or billing logic usually waits.
High-signal MVP capabilities include dashboards that expose care gaps, scheduling insight that predicts no-shows, or AI-assisted documentation that never overwrites clinician notes. Deferrable features include deep order entry, prescription changes, or cross-system record merges. Design your architecture so these deferred capabilities slot in as separate, permissioned modules with their own audits and preconditions.
AI features: when and how to add them?
Add AI once you can show data provenance and define how the model is judged. Doing it earlier hides risk and slows approvals.
As of September 2026, the FDA reported over 1,600 AI-enabled medical devices authorized for marketing in the US. Buyers now ask how AI outputs are monitored and how errors are handled. Build guardrails first: dataset lineage, human-in-the-loop review, override and rollback, and post-deployment monitoring. If your product assists clinical decision making, pilot with narrower indications, then expand. If it is back-office automation, start with audit-only shadow mode before activation.
A practical sequence that avoids rework
An evidence-first sequence reduces late surprises, especially across multiple clinics and EHRs.
- Define the unit of value and its metric. 2) Map the data rights and consent you need to compute it. 3) Build a read-first MVP with immutable audit logs. 4) Pilot at one site with explicit success criteria and a rollback plan. 5) Add constrained writebacks that are reversible and fully logged. 6) Scale with versioned APIs, feature flags, and site-level configuration. For a delivery view that aligns to this, see the Build, Launch, Grow delivery approach.
When do you plan for go-to-market in regulated buyers?
You plan go-to-market alongside integration because contracting and procurement shape scope, data rights, and pricing levers. Leave it to the end and you will rework.
Define who pays and why by the time you exit problem fit. Health systems often require business associate agreements, security questionnaires, and sandbox demos. Partner marketplaces can help but they do not replace site-level approvals. Messaging must map to the metrics you can measure in a pilot, not future-state features. Your sales motion should include a playbook for identity provisioning and training so ops can forecast their workload.
Statistics
- As of September 2026, the U.S. Food and Drug Administration stated that over 1,600 AI-enabled medical devices had been authorized for marketing in the United States. Source: U.S. Food and Drug Administration, Artificial Intelligence-Enabled Medical Devices.
Our take
We think most teams still over-invest in feature velocity and under-invest in consent modeling and EHR provenance, which is why launches slip at the second site. Our view is to bias toward an integration-first MVP with read-only value and immutable audit logs, then add the smallest possible write path with clear preconditions. That sequencing gives InfoSec something they can approve and gives clinicians a way to verify that nothing was silently changed.
Many teams front-load a vendor-agnostic data model and postpone exact integration details. In our experience, that creates brittle assumptions when the first EHR does not expose a field the way your model expects. We would pick one vendor path, pilot read-first, and let the live data shape the model before abstracting. The FDA's figure about AI-enabled devices as of September 2026 confirms that buyers now ask governance questions. Building your audit and consent story first answers those questions with evidence, not promises.
FAQ
What is the end-to-end healthtech product development lifecycle?
It is the path from problem definition to post-market operations, with gates for clinical value proof, compliance architecture, vendor integration, controlled pilots, and scale. Each gate asks for evidence that non-engineers can review, like a data-flow diagram or a pilot result. Teams that front-load these artifacts cut rework and speed site approvals.
How long does it take to reach a read-only MVP?
A focused team can reach a read-only MVP in a few sprints if approvals run in parallel. The schedule often hinges on data access and site onboarding, not code. You can shorten time by scoping the MVP to a single outcome metric, constraining endpoints, and pre-negotiating minimal read rights with one pilot site.
When should HIPAA-focused design start?
Start it before sprint 1 because it decides identities, roles, encryption, logging, and data retention. Adding these late forces rewrites in authentication and storage. Model consent, tenant isolation, and auditability as part of the first architecture review. That also clarifies what you must ask for in EHR integration and what you can defer.
Do I need EHR write access for a meaningful pilot?
Often no. Many pilots prove value with read-only data such as schedules, orders, or clinical notes. Read-first reduces approval friction and lets you validate the metric you claim to move. If you need writes, add them later with narrow scope, queued operations, and a rollback plan that restores prior state if any check fails.
How do AI features change the lifecycle?
They add work in dataset provenance, human oversight, and post-deployment monitoring. Buyers want to know how you judge outputs, handle errors, and log decisions. Add AI after you can trace where data came from and how it is reviewed. Start with shadow mode or assistive features, then enable actions in controlled pilots with clear acceptance tests.
Closing
Map your idea to the six gates, name the evidence each gate needs, and schedule site operations in parallel with code. Start read-first, prove value, then add the smallest safe writeback and scale from there.
The audit is free. Another quarter of guessing is not.
Book the Free 48-Hour Audit