HIPAA compliance in healthtech software development

HIPAA compliance in healthtech software development
HIPAA compliance in healthtech software development means engineering the Privacy, Security, and Breach Notification Rules into your SDLC: identify PHI, apply the minimum necessary standard, enforce access, log everything, and test incident response. As of October 2026, HHS OCR highlighted that teams must run security awareness and training for all workforce members, not just engineers.
Key takeaways
- Bake security awareness and training into sprint rituals, because HHS OCR emphasized this requirement in October 2026 for all workforce members.
- Start EHR integrations read-first, then add constrained writes after consent and reconciliation are proven in production.
- Treat prompts, transcripts, and model outputs as ePHI in AI features. Set retention, redaction, and access controls accordingly.
- Make audit logging a design primitive: who accessed which PHI, when, for what purpose, with immutable storage and searchable context.
- Prove the minimum necessary standard with data maps and query templates that show fields requested, not just endpoints hit.
What HIPAA requires in software development now
HIPAA requires a security awareness and training program for all workforce members as of October 2026, per HHS OCR, and it requires you to design and operate administrative, physical, and technical safeguards across the full data lifecycle.
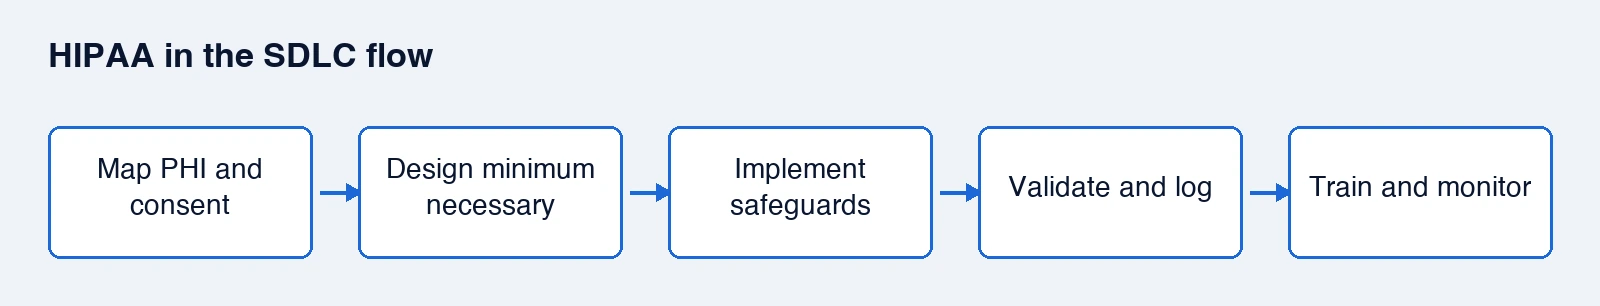
In practice, that means the SDLC must carry HIPAA from planning through operations, not treat it as a document package at launch. Early in discovery, classify PHI flows and the minimum necessary data for each feature. During design, decide where PHI lives, who can access it, and how you will prove that access was appropriate. During build, implement access controls, encryption in transit and at rest, audit logging with purpose-of-use context, and configuration-as-code for policies. During testing, run risk analysis, role-based access tests, and incident simulations. In operations, rotate keys, test backups, review logs, and run recurring workforce training. If you integrate with an EHR, align Business Associate Agreements, consent, and data provenance with each vendor's capabilities and your product's workflow.
Where HIPAA breaks in EHR‑integrated apps
HIPAA breaks most often at EHR integration boundaries where consent, minimum necessary, and reconciliation are unclear.
The fast path to value is usually a read-first integration. It limits PHI exposure while you validate identifiers, patient matching, and consent. Writebacks fail when applications assume broad edit rights or ignore clinic routing rules. That is where breach scope expands, because incorrect writes can replicate across systems and into patient portals. Design for purpose-limited reads, evented sync with provenance, and then narrowly scoped write paths with human-in-the-loop or operational controls. Align the BAA, the EHR's program terms, and your audit model so every data move has a documented basis. If an EHR vendor requires per-tenant approval, plan for that lead time and treat it as a control, not a bottleneck.
For teams evaluating integration shape, the compliance trade-offs are concrete:
| Integration approach | PHI exposure surface | Breach blast radius | Audit and reconciliation needs | Vendor approval risk |
|---|---|---|---|---|
| Read-only FHIR/API | Narrow and observable | Contained to your store | Access logs with query templates; source-of-truth tagging | Lower, often self-service |
| Scoped writeback (appointments, docs) | Moderate and bounded | Affected records plus mirrored portals | Write intent, before/after deltas, correlation IDs, rollback plans | Medium, per-tenant or program-gated |
| Broad writeback (orders, meds, problems) | Wide and complex | Multi-system propagation, difficult rollback | Full provenance, clinical safety review, conflict resolution | High, lengthy approvals |
If your product depends on scheduling, referral, or intake workflows, a read-first path plus evented reads can deliver measurable value while you earn the right to write. When you add writes, constrain them to a single domain with explicit ownership, reconciliation queues, and metrics that show correctness before you scale.
For a deeper run at the vendor mechanics, see our overview of EMR and EHR integration options and pitfalls.
How to design HIPAA‑native AI features
Design HIPAA‑native AI by assuming prompts, transcripts, intermediate embeddings, and outputs are ePHI and handling them with the same controls as clinical data.
Voice agents that schedule or triage, and AI scribes that draft notes, create new PHI at the edge. Treat call recordings and model prompts as sensitive from the first byte. Apply the minimum necessary: redact or tokenize identifiers before sending to a model where possible, and separate routing metadata from content. Put retention limits on raw audio and prompts. Control access with least privilege and break-glass workflows for rare support cases. Log purpose-of-use for each inference or transcription. If you use external model providers, your legal team must evaluate Business Associate Agreement coverage and data use terms before any PHI is processed. For on-premise or virtual private deployments, measure operational realities like GPU utilization, patch cadence, and failover as part of your risk analysis.
When these features update the chart or patient communication channels, add human-in-the-loop checkpoints or constrained write paths, and test for misclassification, hallucinated codes, and template drift. Your workforce training plan should now include agents, prompts, and redaction practices, because HHS OCR emphasized workforce-wide security awareness and training in October 2026.
A live example of balancing operational AI with compliance outcomes is an AI-enabled cardiology system that went live in clinics and was stated to be HIPAA and PIPEDA compliant in its public case study. You can read about the build choices in the cardiology EMR case study.
Proving minimum necessary and purpose of use
You prove minimum necessary by design, not by policy text. The first answer is to request only the fields your feature requires and to formalize that in code and configuration.
Use explicit data maps per feature that list tables, fields, and filters. Back them with API client templates or stored queries that are reviewed like code and tied to feature flags. Add a purpose-of-use field to your access logging so each read and write is linked to an intended workflow and a human or system actor. In reviews and audits, these artifacts show that your product asked for only what it needed, and that you can trace every data access to a justified intent. When a clinic changes its preferences or consent model, you can adjust those templates without rewriting core logic.
Security logging that stands up to audits
An audit log that helps you pass reviews answers who, what, when, where, why, and how for ePHI access.
Capture identity with roles and device fingerprints where applicable. Record the data scope accessed or changed, not just the endpoint. Add purpose-of-use, request origin, and correlation IDs that tie user actions to system events and downstream writes. Store logs immutably with retention aligned to contract and regulation. Make them searchable for threat hunting and incident response. Rehearse incident response with development, support, and management present, because logs only help when people know how to use them. This is also where your workforce training program lives in practice.
Statistics
- As of October 2026, the U.S. Department of Health and Human Services Office for Civil Rights stated that the HIPAA Security Rule requires regulated entities to implement a security awareness and training program for all workforce members, including management. (HHS OCR October 2026 Cybersecurity Newsletter)
Our take
We think most teams over-invest in documents and under-invest in operational controls and workforce training. The October 2026 HHS OCR reminder about security awareness and training is a signal to re-center the program on behaviors you can measure inside the SDLC. Put training outcomes into sprint definitions of done, tie them to real controls like query templates and access reviews, and you will catch drift sooner than a quarterly policy update. We also think teams move to writeback integrations too early. Reads plus evented reconciliation prove identity, consent, and clinical workflow fit with a smaller PHI surface. Only when that holds up in production should you add writes, and even then, scope them to one domain with reconciliation and rollback. The argument is not ideology. It is that blast radius and auditability are functions of data flow shape, and you control that shape by sequencing integration capabilities and training the people who operate them.
FAQ
Does HIPAA apply to my healthtech startup if we never see patients?
Yes, if your product handles PHI on behalf of a covered entity such as a clinic, you are likely a business associate and must meet HIPAA requirements. That includes administrative, physical, and technical safeguards, Business Associate Agreements, and the ability to demonstrate minimum necessary access, audit logging, and incident response.
What is a Business Associate Agreement and when do we need one?
A BAA is a contract that sets each party's HIPAA responsibilities when PHI is handled. You typically need a BAA with any covered entity you serve and with service providers that process PHI for you. Make sure the BAA matches your architecture, including storage locations, subprocessors, and AI model providers if they see PHI.
How should we implement audit logging for HIPAA?
Log access and changes at the data level with identity, timestamp, data scope, purpose-of-use, and correlation IDs. Store logs immutably and make them searchable. Build dashboards for access review and anomaly detection. Test logs during incident response drills to ensure they answer who, what, when, where, why, and how.
Can we use third‑party AI APIs and stay HIPAA‑compliant?
It depends on the provider's willingness to sign a BAA and on their data use terms. Treat prompts, transcripts, and outputs as ePHI. If a provider will not sign a BAA or uses your data for training, you will need an alternative such as a private deployment or a different vendor, plus redaction and retention controls you can verify.
What engineering artifacts help during HIPAA reviews?
Data flow diagrams that show PHI paths, field‑level data maps per feature, access control matrices, audit log schemas with examples, incident response runbooks, and change control records. For EHR integrations, include vendor approvals, consent models, and reconciliation procedures tied to specific read and write operations.
Next steps
Map your PHI flows and minimum necessary fields per feature, implement purpose‑tagged audit logging, and schedule a cross‑functional security awareness and training block in the next sprint. If you plan an EHR integration, begin with a read‑first path and define the consent and reconciliation model before adding writes.
The audit is free. Another quarter of guessing is not.
Book the Free 48-Hour Audit